Fetal Circulation Explained: Blood Flow, Fetal Shunts, and Changes at Birth
From Placental Oxygenation to Neonatal Circulatory Transition and Congenital Heart Disease
CHAPTER 1 — Why Fetal Circulation Is Different
In postnatal life, the right and left ventricles function strictly in series: deoxygenated systemic venous return enters the right heart, passes through low-resistance pulmonary capillaries for gas exchange, and returns to the left heart for systemic ejection. In the fetus, however, the lungs are fluid-filled, metabolically active but non-ventilated, requiring a completely distinct vascular architecture:
The Placenta as the Sole Respiratory Organ
Gas exchange and metabolic waste removal occur in the chorionic villous space. Maternal oxygenated blood equilibrates across thin syncytiotrophoblast layers into the umbilical vein with an oxygen tension (PO2) of approximately 30–35 mmHg (yielding an 80–85% saturation due to the high oxygen affinity of fetal hemoglobin HbF).
High Pulmonary Vascular Resistance (PVR) vs. Low Placental Resistance
Hypoxic pulmonary vasoconstriction and compressive alveolar fluid keep fetal PVR exceptionally high. Conversely, the vast low-resistance placental vascular bed maintains a low Systemic Vascular Resistance (SVR), establishing the pressure gradient that drives right-to-left shunting.
Parallel Ventricular Ejection (Combined Cardiac Output)
Because of the three vascular shunts, both ventricles eject in parallel into a common systemic arterial pool. The fetal heart is measured in Combined Cardiac Output (CCO) (~450 mL/kg/min): the dominant Right Ventricle delivers ~55–60% of CCO, while the Left Ventricle delivers ~40–45%.
CHAPTER 2 — Follow One Drop of Blood: The Complete Circuit
To comprehend fetal hemodynamics, trace a single drop of blood as it travels from maternal gas exchange in the placenta, navigates hepatic branching, streams selectively through the cardiac chambers, and returns to the umbilical cord:
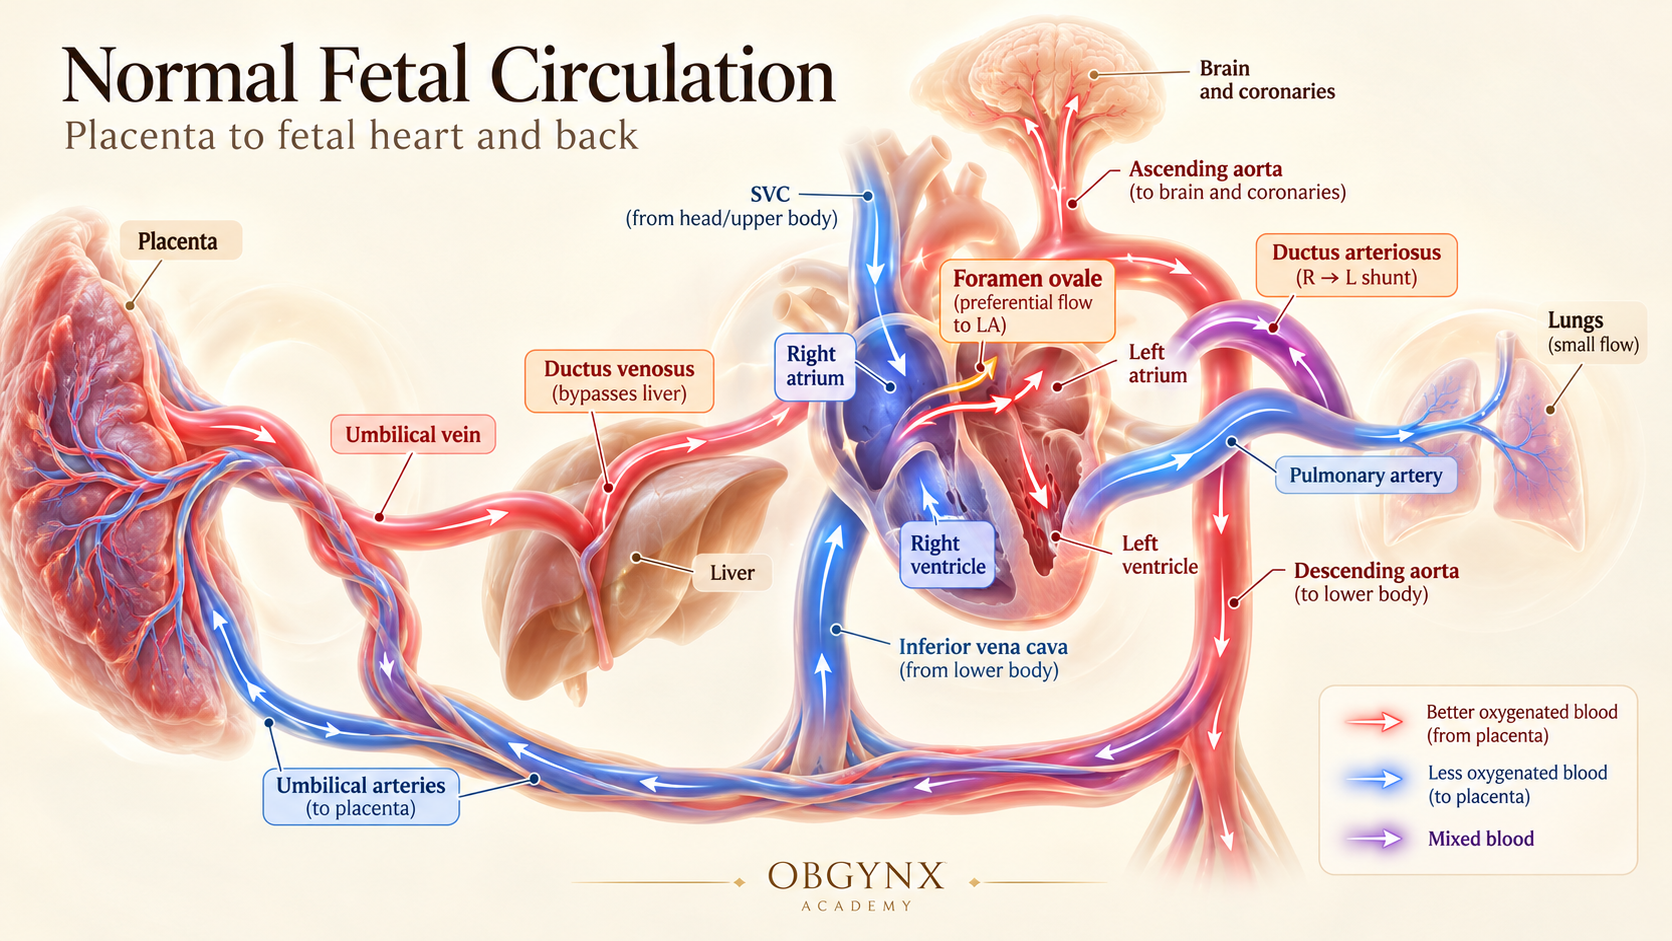
From the placenta via the umbilical vein, ductus venosus, foramen ovale, and ductus arteriosus back through umbilical arteries. Notice the color-coded oxygen saturation gradients (Red = better oxygenated from placenta; Blue = less oxygenated; Purple = mixed blood).
1. Placenta & Umbilical Vein
Highest SaO2 (~80–85%)Oxygen and nutrients diffuse from maternal spiral arteries into fetal villous capillaries. The single Umbilical Vein carries the highest oxygenated blood in the fetus (~80–85% SaO2) into the fetal abdomen.
CHAPTER 3 — The Three Essential Fetal Shunts
Three temporary anatomical shunts redirect fetal blood away from non-functioning organ beds (liver and lungs) to selectively protect cerebral and myocardial oxygenation:
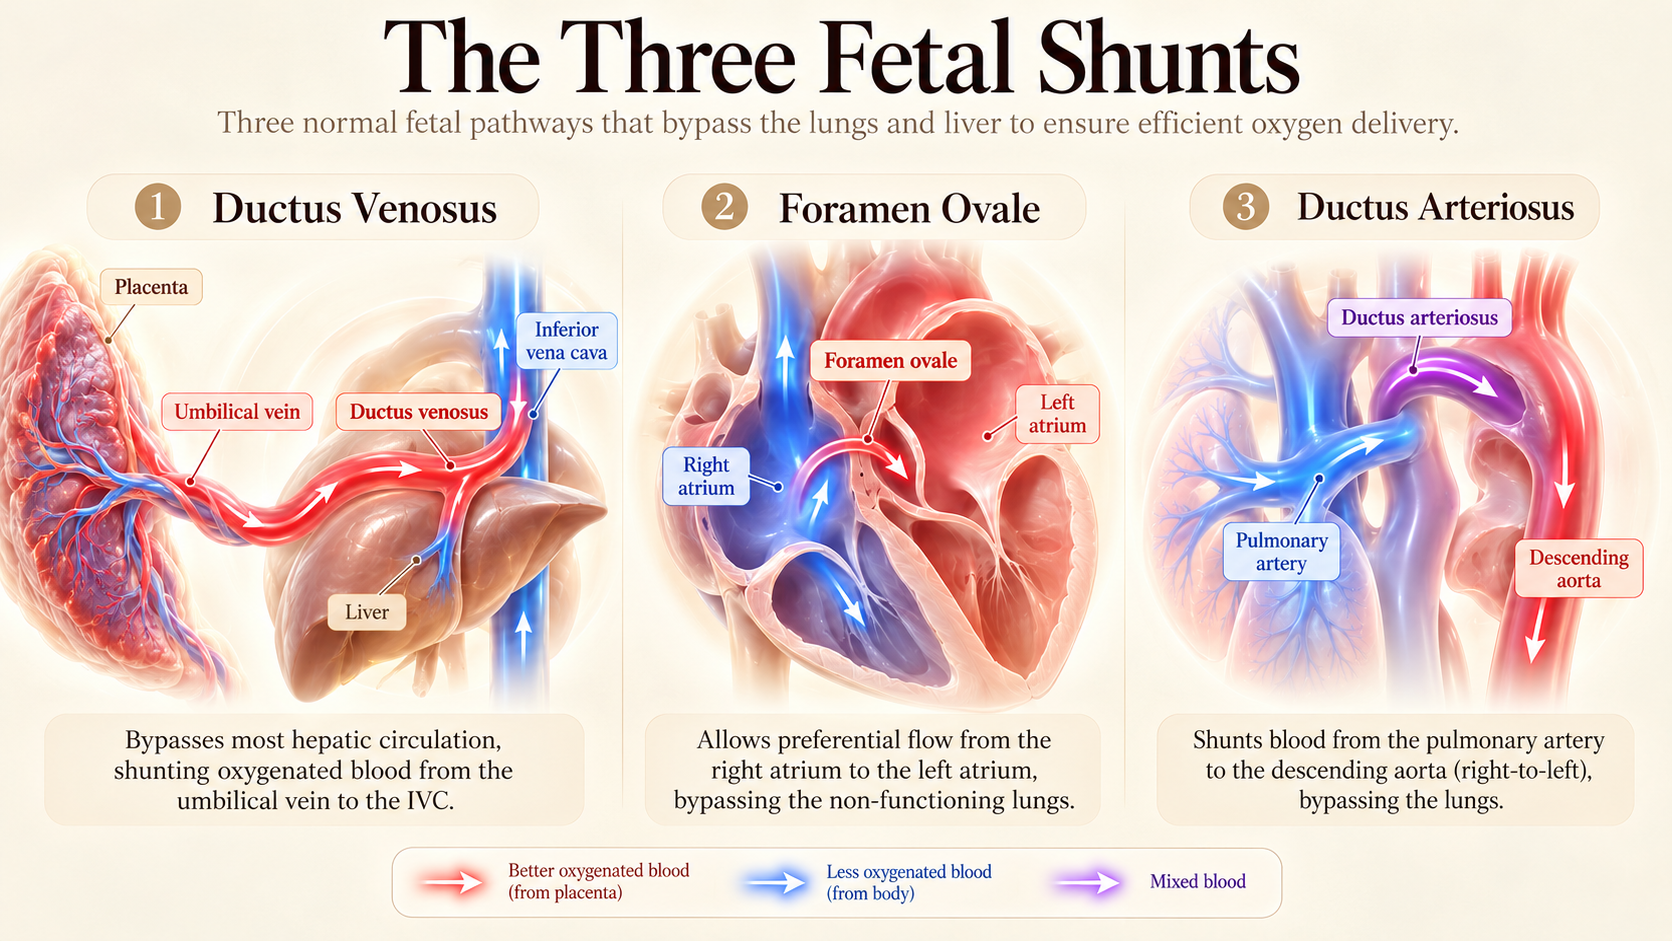
(1) Ductus Venosus: Bypasses the liver to deliver umbilical venous flow to IVC. (2) Foramen Ovale: Preferential right-to-left atrial shunting bypassing the lungs. (3) Ductus Arteriosus: Shunts pulmonary artery blood right-to-left into the descending aorta.
Ductus Venosus (Hepatic Bypass Shunt)
Laminar High-Velocity JetA slender, hourglass-shaped vessel (diameter 1–2 mm at mid-gestation) connecting the umbilical vein to the left hepatic vein near its junction with the IVC.
High forward velocity (50–90 cm/s) with a characteristic triphasic waveform: S-wave (systole), D-wave (early diastole), and positive a-wave (atrial contraction).
CHAPTER 4 — Why the Right and Left Hearts Behave Differently
Unlike adult circulation where cardiac outputs must match stroke for stroke, fetal ventricles manage distinct hemodynamic workloads and deliver different qualities of blood:
Dominant Systemic Contributor
- Handles ~55–60% of Combined Cardiac Output.
- Receives desaturated SVC venous return + abdominal IVC blood.
- Ejects against high PVR, shunting 90% through the ductus arteriosus to lower body and placenta.
Metabolic & Cerebral Guardian
- Handles ~40–45% of Combined Cardiac Output.
- Receives oxygen-rich Ductus Venosus stream via Foramen Ovale.
- Ejects into Ascending Aorta with highest SaO2 (~65%) to supply myocardium and developing cerebrum.
CHAPTER 5 — Fetal Circulation on Ultrasound: The Scanning Planes
Translating physiological flow into sonographic views allows immediate recognition of normal hemodynamics versus critical congenital pathology:
Four-Chamber View (4CV)
Visualizes the flap of the foramen ovale undulating into the left atrium with each cardiac cycle. Confirms right-to-left atrial shunting and equal chamber dimensions (with slight RV dominance in the late third trimester).
Three-Vessel and Trachea (3VT) View
The premier hemodynamic screen: demonstrates the aortic arch and ductal arch meeting at the descending aorta in a classic 'V' shape to the left of the trachea. On color Doppler, both arches must display identical color encoding (concordant antegrade flow toward the spine).
Ductus Venosus Pulsed-Wave Doppler
Obtained in a mid-sagittal or oblique transverse plane. Demonstrates high-velocity triphasic forward flow (S, D, a-wave). A positive a-wave confirms adequate right atrial compliance and normal right ventricular filling pressures.
CHAPTER 6 — What Happens at the First Breath? The Neonatal Transition
At birth, the newborn transitions from placental dependence to autonomous pulmonary respiration in a matter of seconds. Use the interactive comparison below to explore the dramatic physiological reversal:
Lungs unexpanded; hypoxic vasoconstriction keeps blood away.
Placenta receives ~40% of fetal cardiac output.
Eustachian valve directs DV flow into left atrium.
Maintained patent by low PO2 and placental PGE2.
Shunts 50% of umbilical flow to IVC.
Both ventricles pump into common systemic tree.
CHAPTER 7 — Ductal-Dependent Congenital Heart Disease: Why Some Babies Crash After Birth
In utero, fetuses with catastrophic congenital heart malformations appear stable and well-oxygenated because the placenta breathes for them and the patent ductus arteriosus bypasses the obstruction. However, when the ductus naturally constricts after birth, life-threatening collapse ensues:
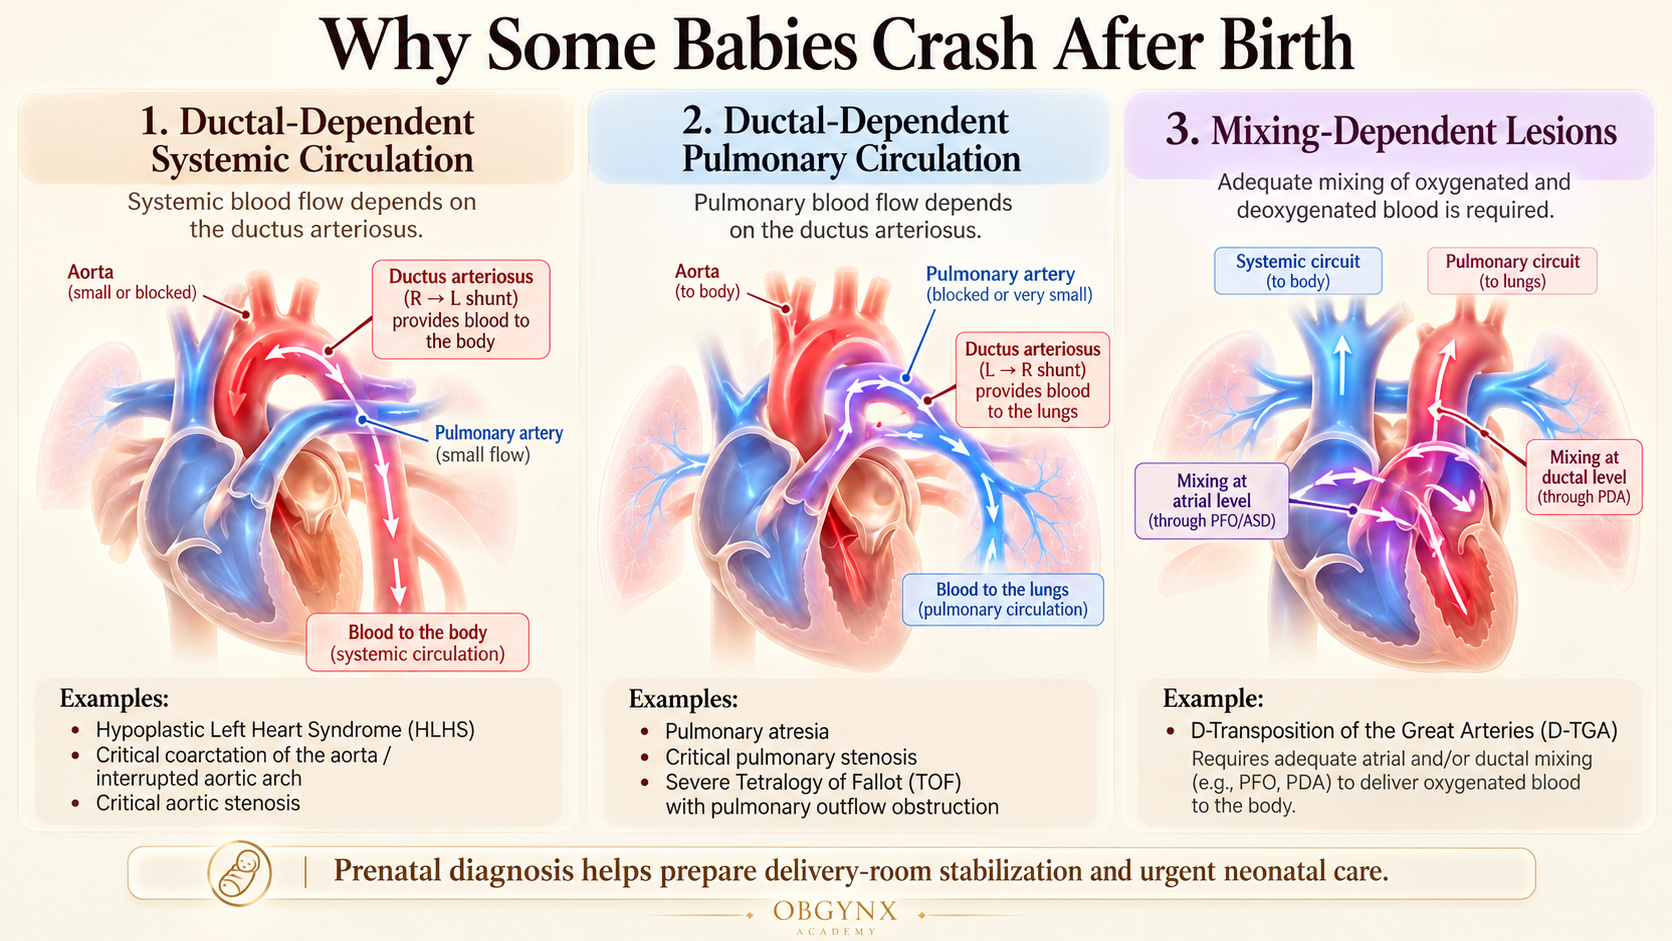
Panel 1: Ductal-Dependent Systemic Circulation (HLHS, Critical Coarctation, Critical Aortic Stenosis). Panel 2: Ductal-Dependent Pulmonary Circulation (Pulmonary Atresia, Critical PS, Severe TOF). Panel 3: Mixing-Dependent Lesions (D-Transposition of the Great Arteries).
Ductal-Dependent Systemic Circulation
R $\rightarrow$ L Ductal ShuntClassic Lesions: Hypoplastic Left Heart Syndrome (HLHS), Critical Aortic Stenosis, Interrupted Aortic Arch, Critical Coarctation of the Aorta.
Mechanism of Collapse: The left ventricle cannot pump blood into the aorta. Systemic perfusion to kidneys, abdominal organs, and legs depends entirely on right-to-left flow across the ductus arteriosus. Retrograde flow from the ductus feeds the ascending aorta and coronary arteries.
Postnatal Emergency: As the ductus constricts within hours of delivery, systemic perfusion collapses, producing cold extremities, anuria, profound lactic acidosis, absent femoral pulses, and cardiogenic shock.
Stabilization: Immediate continuous IV infusion of Prostaglandin E1 (Alprostadil, 0.01–0.05 mcg/kg/min) to reopen the ductus.
CHAPTER 8 — What Fetal Doppler Can Tell Us
Color and spectral Doppler interrogation decode hemodynamic pressure gradients across the fetal cardiovascular tree:
A reversed a-wave indicates that during atrial contraction, blood is forced backwards into the umbilical vein due to abnormally elevated right atrial pressure or severe right ventricular non-compliance. Strongly predictive of impending stillbirth or major cardiac structural defects.
Blood flows backwards (retrograde) in the transverse aortic arch from the ductus arteriosus toward the carotid arteries. Definitive sign of critical left-heart obstruction (HLHS, aortic atresia, interrupted aortic arch).
Blood flows from the aorta into the pulmonary artery across the ductus arteriosus. Indicates critical right-heart obstruction (pulmonary atresia, critical pulmonary stenosis).
CHAPTER 9 — Normal vs Abnormal Circulation: Expert Comparison Matrix
| Circulatory Site | Normal Fetal Finding | Abnormal Finding | Associated Condition | Next Diagnostic Step |
|---|---|---|---|---|
| Ductus Venosus | Forward triphasic flow (positive a-wave) | Reversed or absent a-wave | Severe FGR, Tricuspid regurgitation, Acidemia | Biophysical profile & deliver timing review |
| Foramen Ovale | R $\rightarrow$ L shunting with flap in LA | L $\rightarrow$ R flow or restrictive opening | HLHS, Total Anomalous Pulmonary Venous Return | Targeted fetal echocardiogram & genetics |
| 3VT Ductal Arch | Forward R $\rightarrow$ L flow into descending aorta | Retrograde flow (Aorta $\rightarrow$ PA) | Pulmonary Atresia, Critical PS, Severe TOF | Plan delivery at pediatric cardiac surgery center |
| 3VT Aortic Arch | Forward antegrade flow (left of trachea) | Retrograde flow (DA $\rightarrow$ Arch) | Hypoplastic Left Heart Syndrome, Interrupted Arch | Immediate tertiary center delivery with PGE1 |
| Ductus Arteriosus | Wide caliber, PI > 1.9, Peak < 140 cm/s | High velocity, PI < 1.9, constriction | Premature ductal closure (Maternal NSAIDs) | Stop maternal NSAIDs; evaluate RV strain |
CHAPTER 10 — Prenatal Diagnosis to Postnatal Planning
Why does prenatal diagnosis of circulatory dependence matter? Newborns diagnosed before birth have drastically lower rates of pre-operative metabolic acidosis, end-organ failure, and neonatal mortality compared to those diagnosed after circulatory collapse:
Delivering at an institution with on-site pediatric cardiothoracic surgery avoids high-risk emergency neonatal transport in shock.
Prostaglandin E1 is pre-drawn and initiated through an umbilical venous catheter immediately after cord clamping, preventing ductal constriction.
Simultaneous pulse oximetry on the right hand (pre-ductal) and lower extremity (post-ductal) accurately quantifies ductal shunting and differential cyanosis.
Coordinated obstetrical, maternal-fetal medicine, neonatology, cardiac intensive care, and congenital heart surgery protocols established weeks prior to term.
CHAPTER 11 — 10 Clinical Pearls and Common Diagnostic Pitfalls
CHAPTER 12 — Frequently Asked Questions in Fetal Circulation
What are the three fetal shunts and their postnatal remnants?
The three shunts are: (1) Ductus Venosus (becomes ligamentum venosum), (2) Foramen Ovale (becomes fossa ovalis), and (3) Ductus Arteriosus (becomes ligamentum arteriosum).
Why is fetal circulation described as operating in parallel rather than in series?
Because blood from both ventricles empties into the systemic arterial pool via the foramen ovale and ductus arteriosus, allowing the right and left ventricles to share the systemic workload according to vascular resistance rather than strict serial volume.
What causes the ductus arteriosus to close after birth?
The sudden increase in systemic arterial PO2 (from ~25 mmHg to ~100 mmHg) combined with the sharp withdrawal of circulating placental prostaglandins (PGE2) triggers intense smooth muscle contraction of the ductal wall.
Why does blood bypass the fetal lungs in utero?
The fetal alveoli are collapsed and fluid-filled, causing hypoxic pulmonary vasoconstriction and very high pulmonary vascular resistance (PVR). Blood follows the path of lower resistance through the ductus arteriosus directly to the placenta.
What is the clinical significance of a restrictive foramen ovale?
If the foramen ovale is small or restrictive (<2 mm), oxygen-rich blood cannot enter the left atrium, potentially causing left ventricular hypoplasia or immediate fatal hypoxemia in d-TGA after birth.
How does prenatal diagnosis of ductal-dependent lesions improve neonatal outcomes?
It allows planned delivery in a pediatric cardiac surgical center, immediate initiation of Prostaglandin E1 before the ductus closes, and prevention of cardiogenic shock, metabolic acidosis, and hypoxic-ischemic brain injury.
From Fetal Circulation to Neonatal Survival: The OBGYNX Takeaway
Fetal circulation is a masterwork of biological adaptation designed to deliver high-oxygen blood to the brain and myocardium while shunting volume away from fluid-filled lungs to the low-resistance placenta. When an anatomical defect obstructs ventricular outflow, the patent ductus and foramen ovale mask the pathology until cord clamping triggers the neonatal transition.
Concordant antegrade flow in the 3VT view confirms normal ventricular ejection. Any retrograde flow is diagnostic of ductal dependence.
Differentiate ductal-dependent systemic (HLHS/CoA) vs. pulmonary (PA/PS) vs. mixing (d-TGA) vs. obstructed venous (TAPVR).
Prostaglandin E1 initiated in the delivery room eliminates pre-operative mortality and protects neonatal neurodevelopment.
Clinical Knowledge Checks (8 Questions)
Which fetal vascular structure carries the highest oxygen saturation (~80–85% SaO2) in the entire fetal circulation?
What is the primary hemodynamic mechanism responsible for shunting oxygen-rich Ductus Venosus blood across the Foramen Ovale?
In normal fetal circulation, what is the predominant direction of blood flow across the Ductus Arteriosus?
Immediately after the first breath and umbilical cord clamping, what primary event causes functional closure of the Foramen Ovale?
In Hypoplastic Left Heart Syndrome (HLHS), which physiological shunt is mandatory for sustaining systemic perfusion to the body?
What does detection of retrograde (reverse) flow in the Ductal Arch on the Three-Vessel-Trachea (3VT) view indicate?
Why can administration of Prostaglandin E1 (Alprostadil) worsen clinical status in obstructed Total Anomalous Pulmonary Venous Return (TAPVR)?
Which maternal medication class is well documented to risk premature in-utero constriction of the fetal Ductus Arteriosus?
Primary Scientific References & Literature Sources
- Morton SU, Brodsky D. Fetal Physiology and the Transition to Extrauterine Life. Clin Perinatol 2016; 43(3): 395–407. [NCBI Bookshelf NBK539710]
- Banka P, et al. Embryology, Fetal Circulation. StatPearls Publishing 2023. [NCBI Bookshelf NBK537149]
- American Society of Echocardiography. Guidelines and Recommendations for Performance of the Fetal Echocardiogram. J Am Soc Echocardiogr 2023. [ASE Guidelines 2023]
- Carvalho JS, et al. ISUOG Practice Guidelines (updated): fetal echocardiography screening. Ultrasound Obstet Gynecol 2023; 61: 788–803. DOI: 10.1002/uog.26224
- Rudolph AM. Congenital Diseases of the Heart: Clinical-Physiological Considerations. 3rd ed. Wiley-Blackwell 2009.